Saturday, November 21, 2026

Has North Carolina No Decency Regarding Iryna Zarutska?

This Democrat-run state enabled Iryna's vicious murder and has done everything in its power to make sure that neither her name or her beautiful face are remembered and memorialized. The murals in her memory are still up in NC, but in other cities they have been vandalized or removed. And NC is trying to have the wrongful death suit by her grieving Ukranian parents thrown out.

As usual, the criminal and the murderer receives sympathy, while the victim is erased.

------------------------------------------------ 

Forgetting the lessons of Iryna Zarutska's murder

NY Post Editorial Board, 11-21-26

An image collage containing 1 images, Image 1 shows Portrait of Iryna Zarutska with blonde hair and a white top
Iryna Zarutska case leaves no question of the city's moral guilt         

Charlotte, NC, may get a judge to toss the wrongful-death suit over the horrific 2025 murder of Iryna Zarutska on a light-rail train, but the news that continues to break about the case leaves no question of the city’s moral guilt, even as the state seems poised to forget what lessons it did take from this nightmare.

The city is arguing that the serial public-safety failures that enabled career criminal DeCarlos Brown’s slaughter of the Ukrainian refugee fall under the cover of government immunity — that is, that it can’t be held liable for official acts such as setting its overall transit-policing strategy, and specifically its use of private-security contractors, not actual cops, to patrol the light rail. 

Yet Charlotte admits 1) that Brown managed to board the train with no ticket, and 2) that there was no private-security guard in that train to stop him from stabbing Zarutska in her neck, leaving her to bleed out in a car full of frozen fellow passengers.

And the system failures go much farther than that.

Brown was a violent thug with a mile-long rap sheet, arrested and released at least 14 times over a decade-plus for crimes like assault, felony robbery and firearms possession. 

Many of them took place in Mecklenburg County, where the lefty MacArthur Foundation had spent big bucks “to continue safely reducing the jail population.”

Fourteen chances to save Iryna’s life, all wasted by a blue-city “justice” system bent on maximum leniency for violent criminals.

If that doesn’t justify a wrongful death suit, it’s hard to imagine what might. 

More: Brown’s documented history of mental illness left him a ticking time bomb with his schizophrenia ignored — at least until after Iryna bled out at his hands.

Indeed, then-Charlotte Mayor Vi Lyles’ initial response to the crime devoted a single sentence to Iryna (not even by name), spending far more words on sympathy for her killer because of a vague mental-health “crisis.”

The state later used Brown’s insanity to justify not putting him on trial on charges that could mean life in prison — a final insult to the memory of the woman he murdered. 

The one small ray of light here was North Carolina’s 2025 passage of “Iryna’s Law,” restricting cashless bail and easing involuntary commitment. 

But the bulk of the state’s Dem lawmakers voted no or abstained — and Democrats just won control of North Carolina’s lower house and near-parity in the upper: Expect them to roll back those reforms. 

None of the judges who let Brown out over and over and over and over will be held responsible for Iryna’s murder, nor the lawmakers who made it so easy to leave him walking free, nor the local officials who left her exposed on that train.

Instead, the people of North Carolina — indeed voters across the nation — just chose to empower the party that demands such contempt for public safety.

Get ready for more horrors like the killing of Iryna Zarutska.

Friday, November 20, 2026

A Rise in COVID in Wastewater, in Time for Thanksgiving

By Cole Mercer at Medical Daily 11-19-26

 
The amount of virus that causes COVID-19 in U.S. wastewater rose 9% between Oct. 31 and Nov. 7, according to CDC data compiled by The Sick Times in its weekly national review. The increase reverses the decline seen in late October, and the CDC rates national wastewater activity as moderate and slightly increasing.

The rise is not limited to one region. As of Nov. 12, CDC models estimated that infections were growing or likely growing in 37 states, including every Midwest state, while wastewater levels climbed sharply in Colorado, Utah and Montana.

For families planning Thanksgiving on Nov. 26, the timing matters. Millions of people will travel and gather indoors next week. Wastewater cannot show who is sick, but it can show whether the virus is becoming more common where a visit is planned. That is useful for households that include an older relative or someone with a weakened immune system.

A Reversal From Late October

MedicalDaily previously reported on elevated October levels in Massachusetts and Connecticut. At that time, the CDC's national wastewater measure had fallen 17% in late October, while WastewaterSCAN reported a 12% increase over a slightly earlier week, according to an earlier Sick Times review of national trends. The CDC has since revised its data and now shows increases for both the weeks ending Oct. 31 and Nov. 7.

Two other wastewater networks point the same way. WastewaterSCAN, a national monitoring program, reported a 9% rise between Oct. 28 and Nov. 4 and rated its national level high. Biobot Analytics reported rising levels nationally and in most regions.

Clinical data tell a slightly different story. CDC test positivity fell from 3.7% to 3.3% over the same week. Indicators do not always move together, and far fewer people test for COVID-19 than in earlier years.

Betsy Ladyzhets, who tracks state and national dashboards for The Sick Times, noted that unlike the past couple of years, there has been no real lull between the summer and early fall wave and the rise heading into winter.


Midwest, Mountain West and Hot Spots in the East

In the Midwest, wastewater levels remain below the national average but are rising, and CDC models show growing infections in all Midwest states. Wastewater and test positivity data also suggest possible increases there.

The West is mixed, with declines along the coasts and increases inland. Colorado, Utah and Montana show large wastewater increases, and CDC models report definite case growth in those states. The latest data suggest COVID-19 may be rising again in California.

Other regions already sit higher. The CDC lists wastewater levels as very high in Florida, Virginia, Kentucky, Arkansas and Washington, D.C., as well as in Connecticut, Massachusetts and Vermont. Connecticut's statewide average is its highest in more than a year, and some Florida sites are higher than during the summer wave. Test positivity and emergency department visits remain below summer peaks for much of the South.

New York is listed as very low, but recent New York City data were not available, so that reading may not reflect the city. Readers can check their own state on the CDC's national and state wastewater data page, which updates every Friday with the previous week's results.


Reading Wastewater Data Before the Holiday

Wastewater surveillance measures virus shed by everyone connected to a sewer system, including people who never test or see a doctor and people without symptoms. That is why health officials use it as an early warning of community spread.

It also has limits. Wastewater cannot count cases, identify who is infected or predict how severe a wave will be. The CDC's figures are preliminary, and a single week's change can be revised, as the agency's own late-October figures were. The CDC's activity levels are also based only on measurements from the past two years. A contract change is causing a brief data gap at about 200 sites, and states marked "limited coverage" have results representing less than 5% of their population.

That is why trends over two or three weeks are more useful than one number. A rising line in the community where a family is gathering is a reasonable signal to add precautions. A single high reading in a distant state is not.

The data also do not identify which variant is driving the increase. The latest Sick Times review did not report on variants, and MedicalDaily did not find an official update linking the rise to a new strain.


Protecting Higher-Risk Relatives

Most healthy adults recover from COVID-19 at home. Older adults face the highest risk of severe illness, and the risk also rises for people with weakened immune systems, heart, lung or kidney disease, diabetes, and other chronic conditions, according to the CDC's list of COVID-19 risk factors. Pregnancy also raises the risk.

Households can take low-cost steps. A rapid test on the day of a visit, or on two days in a row, can catch some infections, though a negative result does not rule out COVID-19. Staying home when sick, opening windows, and spreading out seating lower exposure indoors.

Older adults who develop symptoms should contact a clinician quickly, because COVID-19 antiviral pills work best when started within the first few days of illness. Updated 2026-27 COVID-19 vaccines are available at pharmacies and clinics. Eligibility and insurance coverage vary, so a pharmacist can confirm whether a dose is recommended. Flu is also running early, with activity higher than usual for this time of year, so families can ask about flu shots at the same visit.

Trouble breathing, persistent chest pain, new confusion, or bluish lips require emergency care. The CDC posts new wastewater data each Friday, and MedicalDaily will report whether the national level moves above moderate before or after Thanksgiving.

Melanie Phillips on Britain's War On Israel

Here's the latest column by Melanie Phillips. The British government should be looking out for its own citizens, not obsessing over and attacking Israel constantly and dreaming of their delusional "two-state solution".

--------------------------------------

Miliband’s murderous solution. The British government is continuing to perpetuate a truly infernal legacy.

Melanie Phillips, JNS, 11-19-26

"Faced with apparently intelligent individuals spewing demonstrably ridiculous lies—Israel is committing genocide, Gaza is drowning, half a million Jews are ethnic-cleansing terrorists—a natural response is to wonder if they’ve all simply lost their minds.

"Reasonable people may conclude that, since smart people can’t possibly believe what they’re saying, they’re obviously playing some kind of cynical or opportunistic game.

"But what if they actually do believe what they’re saying?

"In Britain, Andy Burnham’s Labour Party government has effectively declared war on Israel.

"Britain’s Foreign Secretary, Ed Miliband, has sanctioned eight construction and property development companies involved in Israeli “settlement” expansion, limiting their access to finance and ability to support further building in the “West Bank” territories of Judea and Samaria.

"While few such companies stand to suffer directly, this is just the start. The real danger for Israel is that Britain and other hostile Western countries start targeting banks and other institutions funding Israeli projects that may include large towns such as Ariel, Efrat or Ma’ale Adumim, which are beyond the 1948 ceasefire lines but are strong members of Israeli society.

"In other words, this is an attack that will harm Israel itself.

"Some half a million Jews live in Judea and Samaria, and a further 250,000 live in the disputed Old City, the site of the First and Second Temples and the epicenter of religious Judaism. These measures are designed to force the Jewish residents out on the spurious grounds that their presence in their ancient homeland is illegal. It is not; it is legal many times over.

"And, of course, this defamation will put British Jews who are under siege from a climate of unhinged attack at even greater risk.

"The Burnham government is stoking an already murderous hysteria against Israel and Jews. It will also further embolden Britain’s own Islamists, who, like their counterparts in America and across the West, are delirious with excitement.

"They believe that the support of Western dupes like Burnham and Miliband, the rise to power in America of New York Mayor Zohran Mamdani and Michigan senator-elect Dr. Abdul el Sayed, and the Democratic Party falling like dominoes to Islamist activists show that they’re now within reach of the destruction of Israel and the conquest for Islam of Britain, America and the West.

"An angry Miliband claimed the presence of Jewish residents in Judea and Samaria will prevent the establishment of a Palestinian state, thwarting a “two-state solution” he thinks is the only way to end the Middle East conflict.

"That doesn’t hold water. Israel is 18% Arab; why can’t a Palestine state have Jewish citizens? Miliband is actually punishing Israel for not supporting the ethnic cleansing of Jews to make the land Judenrein for a future Palestine state.

"He uttered not a word about the daily Arab assault on Jews in these disputed territories. On Wednesday alone, the Judea and Samaria Situation Room reported five terror attacks on Israelis. Instead, Miliband refers in general to Jewish residents of these areas, almost all of whom are blameless for any violence, as “settler terrorists.”

"He called the E1 building project to link Ma’ale Adumim with Jerusalem “unconscionable.”

"What’s really unconscionable is the British government’s continued funding of the Palestinian Authority, despite its “pay for slay” reward policy for the terrorist murder of Israelis and despite teaching its children, year in, year out, that their highest calling is to murder Jews.

"What’s really unconscionable is Miliband’s repeated demonization of Israel with wicked falsehoods. He has falsely accused Israel of blocking “desperately needed aid” and deepening “the intolerable suffering of civilians in Gaza” after recent flooding added another pressure to their lives—lives that are run by Hamas, not Israel.

"Not a word from him to acknowledge what even Fatah has confirmed—that Hamas has been stealing the tens of thousands of tents and tons of other supplies that Israel has allowed into Gaza in this crisis.

"What’s really unconscionable is how he’s actively helping Hamas by joining the foreign ministers of Australia, Canada and Italy in their call for “dual-use items necessary for humanitarian operations and early recovery” to be granted entry into Gaza.

"These include tent poles that Israel has banned, saying Hamas would exploit them for military purposes. Who can doubt this, when Hamas even tore up Gaza’s water pipes to turn them into rocket parts?

"It’s assumed that Burnham is feeding Israel into the hungry jaws of his own hard-left and the “Gaza First” Muslim bloc, which now boasts five members of parliament and is snapping at the heels of scores of Labour lawmakers.

"Undoubtedly, these are relevant factors. But the reality is almost certainly even more baleful. It’s all too likely that Burnham and Miliband really do believe what they’re saying.

"Miliband’s Jewish identity is fractured and confused. His assertion that these sanctions will only affect the settlements and not Israel, whose prosperity he claims to support, is clearly ridiculous. But mixing as he does with post-Zionist Jews, he may really believe that what he’s doing is—diabolical as this may sound—a moral Jewish response.

"To get your head round this monstrous distortion, it’s necessary to understand the mindset of the entire Western progressive class, including post-Zionist Jews.

"Their core belief is the fantasy of creating the brotherhood of man, in which there are no nations and no religions to divide us and—in the words of John Lennon’s song “Imagine”—nothing to fight or die for.

"Every conflict can be solved by negotiation and compromise. In their culture of moral relativism in which there’s no objective good or bad, right or wrong, the only thing that matters is the consequences. Wars must be avoided, as that means dead people. So Israel must negotiate a solution with the Palestinians.

"The fact that Palestinian Arab identity is itself constructed around the extinction of the Jewish presence in the land of Israel is simply blanked out. It can’t be allowed to get in the way of the unshakeable liberal belief that everyone in the world only wants a nice job, a nice family and a nice life.

"Believing in nothing very much themselves, trapped in their bubble of narcissistic hedonism, such liberals cannot begin to grasp the strength of fanatical Islamic religious belief that seeks the annihilation of Israel and the death of Jews. They say that war solves nothing (World War II, anyone?) and the only solution is through negotiated settlement.

"That’s why Miliband is obsessed with the two-state solution, which he described as “the ‘North Star’ of this government’s approach” to Israel and Palestinian Arabs.

"The fact that a state of their own has already been offered and rejected by the Palestinian Arabs five times—and that a Palestinian state would put all of central Israel within firing range from the strategic hilltops of Judea and Samaria—means nothing to him at all.

"What he so signally fails to grasp is that the unending Middle East impasse that obsesses him beyond all else was actually created by his own country through precisely the strategy he is now demanding Israel accepts.

"For Britain pioneered the “two-state solution” twice. First, when Winston Churchill hived off three-quarters of Palestine, which had all been designated for the Jewish homeland, to carve out Jordan for the Hashemite Arabs. And second, when it tried unsuccessfully to palm off to the Arabs much of what was left of Mandate Palestine to stop them from murdering even more Brits and Jews.

"This reward to the Palestinian Arabs for genocidal terror, which has remained the strategy of Britain and the West ever since, has incentivized them to continue to try to wipe Israel out in the certainty that Britain and the West will punish the Jews ever more severely for resisting.

"Britain is therefore the original creator of this terrible conflict, and has much Israeli and Arab blood on its hands as a result. Burnham and Miliband are merely continuing to perpetuate a truly infernal legacy."

-------------

Melanie Phillips, a British journalist, broadcaster and author, writes a weekly column for JNS. Currently a columnist for The Times of London, her new book, Fighting the Hate: A Handbook for Jews Under Siege, has just been published by Wicked Son. Her previous book, The Builder’s Stone: How Jews and Christians Built the West and Why Only They Can Save It, was published in 2025. Access her work at: melaniephillips.substack.com.

Thursday, November 19, 2026

COVID and People Over 65

Here's an informative article from the National Council on Aging 

I Have COVID. Now What? A Guide for Older Adults

Nov 13, 2026

You took a COVID-19 test, and it’s positive. Or maybe you have a fever, dry cough, and scratchy throat and think it may be COVID. Either way, you’re probably wondering: What should you do next?

If you’re an older adult, it’s vital to take early action—even if your COVID symptoms seem mild. Age is one of the biggest risk factors for severe illness; in fact, people 65 and older face a much greater chance of becoming seriously ill. Your first steps should include staying home, resting, contacting your doctor, and asking about COVID treatment. Some treatments must be started within a few days to be effective.

What to Do If You Have (or Suspect) COVID-19

1. Stay home

Avoid close contact with others while you're sick.

2. Get testedTake a COVID test. If it's negative but you have symptoms, test again in 48 hours.
3. Ask about treatmentContact your health care provider promptly. COVID antivirals must be started within 5-7 days after symptoms begin.
4. Manage mild COVID symptomsRest, drink fluids, and ask which over-the-counter medicines are safe for you.
5. Protect othersTake extra precautions after you return to normal activities, like washing your hands and wearing a well-fitting mask.
6. Know the warning signsCall 911 if you have trouble breathing, chest pain or pressure, confusion, low alertness, or pale, gray, or blue skin, lips, or nails.
7. Monitor your healthWatch for symptoms that worsen, return, or interfere with daily activities. Reach out to your doctor with concerns.

Find out what to do after testing positive for COVID during the 2026 respiratory season, including how to manage COVID symptoms at home, protect others, and recognize warning signs that you may need medical care.

What should I do first if I have COVID?

If you have COVID symptoms or test positive, stay home and away from other people as much as possible. No matter what you’ve got going on in your life, give yourself permission to slow down and rest.

It’s also wise to contact your doctor’s office or health clinic, especially if you’re 65 or older or have a chronic health condition like diabetes or heart disease. These factors put you at higher risk for severe COVID-related illness, complications like pneumonia, and even death. 

“Don’t wait until you feel really sick to make that call,” advised Dorothea Vafiadis, NCOA Senior Strategist for Healthy Aging. “Think about when your COVID symptoms first started and write down the date if you can. Your doctor or nurse will need this information to determine if you’re within the window for antiviral treatment.”

Should I get tested for COVID?

Yes. If you have symptoms of illness, testing can help you find out if COVID-19 is the likely cause. A definitive diagnosis will allow you to make informed decisions about treatment and protecting those you care about. You can use an at-home rapid antigen test or request testing at your doctor’s office, health clinic, or local pharmacy (available at some locations). A positive result means the SARS-CoV-2 virus was detected and you have (or recently had) a COVID infection.

What if your test is negative, despite having COVID symptoms? One negative result doesn’t necessarily rule out COVID. According to the U.S. Food and Drug Administration (FDA), you should “always do a repeat test 48 hours after a negative result on an antigen test.”

See NCOA’s guide to COVID testing for older adults.

Should I ask about COVID treatment?

Yes. If you’re an older adult, it’s worth asking your doctor or nurse if there’s a COVID treatment that could benefit you.

Antiviral medications are shown to lower the risk of hospitalization and death in people at elevated risk, like older people or those with chronic diseases. Antivirals do not shorten the duration of COVID symptoms. 

When it comes to oral antiviral treatments for COVID, Paxlovid is usually the first line of defense. In clinical trials, Paxlovid was found to be 88% effective at lowering the risk of COVID-related hospitalization. Lagevrio (molnupiravir) is another oral antiviral treatment that's often used when Paxlovid is not available or deemed inappropriate for a patient.

Both Paxlovid and Lagevrio must be started within 5 days after symptoms begin. Veklury (remdesivir), a 3-day intravenous (IV) infusion treatment for COVID, must be started within 7 days of symptom onset. Your doctor can suggest the best option for you based on your age, symptoms, and overall health.

Timely treatment can make all the difference in your recovery. That’s why you should reach out to your doctor’s office or clinic as soon as you know or suspect you have COVID. See our guide to COVID antiviral treatment.

How can I manage COVID symptoms at home?

When recovering at home with a mild case of COVID, be sure to make rest a priority. Resting helps direct your body’s energy toward clearing the virus instead of everyday tasks. You’ll also want to consume plenty of liquids to help ease nasal irritation and replace fluids lost through sweating, coughing, and congestion. 

Over-the-counter (OTC) medicines, like acetaminophen (Tylenol) or ibuprofen (Advil), can help relieve fever, headaches, and body aches when they’re safe for you to take. But before using any OTC medicine, check with your doctor or pharmacist to see if they might interact with your regular medications or affect an existing health condition.

If you’re taking a prescription medication, don’t abruptly stop or change the dose on your own. Always check with your doctor or pharmacist first.

How do I protect others if I have COVID?

Since COVID-19 spreads from person to person, you’ll need to take extra care around others while you’re sick. The Centers for Disease Control and Prevention (CDC) recommends that you: 

  • Stay home and away from other people until your symptoms are improving overall, and you’ve been fever-free for at least 24 hours (without taking fever-reducing medicine like Tylenol or Advil). 
  • Take extra precautions for the next 5 days after you return to your usual activities. These may include wearing a well-fitting mask, improving indoor ventilation, keeping some distance from others, and washing your hands often and thoroughly.
  • Be especially careful around people who are at higher risk for severe illness—like older adults or those with chronic health issues. 

When should I call my doctor about COVID?

Make note of how you feel from day to day. Contact your doctor or nurse if your symptoms are getting worse instead of better or if you’re worried about how you’re recovering.

For example, call if you’re having breathing problems, you’re becoming dehydrated, a fever lasts several days, or symptoms improve and then return or worsen. “You should also reach out if COVID seems to be making one of your existing health conditions worse,” Vafiadis said. “For instance, if you have asthma and you’re wheezing more than usual or you need your inhaler more often.”

When is COVID an emergency?

Some COVID symptoms require immediate medical attention. Call 911 or have someone bring you directly to the hospital if you have:

  • Trouble breathing
  • Chest pain or pressure that doesn’t go away
  • Difficulty waking up or staying awake
  • Sudden, unexplained confusion 
  • Pale, gray, or blue-colored skin, lips, or nail beds, depending on your skin tone

If you have symptoms not on the list above that feel severe or life-threatening, it’s best to seek emergency medical care.

What if my COVID symptoms go away and come back?

Sometimes COVID symptoms return after you’ve started feeling better. You may even get a positive test again after testing negative. This is known as COVID rebound.

Rebound typically occurs 3 to 7 days after the initial illness has resolved, and it can happen whether or not you took an antiviral medication. Fortunately, COVID rebound symptoms are usually mild and clear up within a few days—and they don’t mean you’re at greater risk for severe illness.

If you think you may have COVID rebound, check in with your doctor or nurse.

What should I do after I recover from COVID?

COVID recovery looks a little different for everyone. You may bounce back fairly quickly, or it may take some time before you feel back to 100%.

“Pay close attention to how you’re feeling as you recover, especially your energy level and breathing,” Vafiadis explained. “If symptoms linger, if they come back, or they make it hard to manage your usual activities, let your doctor know.”

Some people develop a condition called long COVID, which can cause a variety of life-disrupting symptoms that last for months or longer following an initial COVID infection.

Susan struggled with long COVID for more than two years, suffering from headaches, fatigue, memory loss, and fever. She has since regained her health, but makes it a point to warn others: “… It’s vital to remember that viral infections are debilitating or even deadly,” Susan said, sharing her story with the World Health Organization (WHO). “I hope people are now better at minimizing contact with others if they have viral symptoms and more readily take up protective vaccinations when offered.”

Do older adults still need a COVID vaccine?

Yes. Current CDC guidance recommends a 2026-2027 COVID-19 vaccine for all adults ages 18 years and older. Adults 65 and older are advised to get two doses of the updated vaccine, six months apart, even if they’ve been vaccinated before. That’s because seniors in this age group face a much higher risk of serious COVID illness, hospitalization, and death. 

Ask your doctor, nurse, or pharmacist about your personal risks and when to get your COVID, flu, and RSV vaccines, if you haven’t already. 

Want to learn more? Explore our COVID-19 Safety and Protection resource library.

Frequently asked questions (FAQ)

How soon should I call my doctor after testing positive?
If you’re an older person or have other risk factors for severe COVID, call your doctor’s office or health clinic as soon as possible. To be effective in reducing the risk of severe illness and hospitalization, COVID treatments need to be started within a few days after COVID symptoms begin.

Do older adults need COVID treatment?
Not everyone needs treatment for COVID, but older age increases your risk for serious, even life-threatening illness. Your doctor or nurse can help determine if antiviral treatment is appropriate for you based on your age, COVID symptoms, and health.

How long is COVID contagious?
You can spread the virus for a day or two before COVID symptoms start, and you’re usually most contagious around the time you first feel sick. Most people are no longer contagious after about 8 to 10 days, though people with weakened immune systems may spread the virus for longer.

How long should I stay home if I have COVID?
You should stay home until your COVID symptoms are improving overall and you’ve been without a fever for at least 24 hours without taking a fever-reducing medicine (e.g., Tylenol, Aleve, Motrin). Then, take added precautions for the next 5 days or so, such as wearing a well-fitting mask or testing when you know you’ll be around other people.

Can I take my regular medications with COVID treatment?
It depends. Some COVID treatments, like Paxlovid, can interact with other medicines. Make sure your doctor, nurse, or pharmacist knows about all the medications you take regularly. This includes prescriptions, over-the-counter medicines, vitamins, and supplements.

What are signs COVID is getting worse?
Watch for a steady or returning fever, signs of dehydration (e.g., dark-colored urine, urinating less often, dry mouth), increasing breathing problems, or symptoms that improve and then get worse. Call 911 or go to the emergency room for severe difficulty breathing, persistent chest pain or pressure, sudden confusion, or trouble waking up or staying alert.

Wednesday, November 18, 2026

Anti-American, Anti-Israel Sabotage

It's not insanity and he's not a "lunatic".  He knew exactly what he was doing, and he did it out of pure spite and rabid hatred of Israel and the United States, because he's supposedly a "peace activist."

$60 million dollars down the drain thanks to his hateful ideology.

-------------------------------------------------------- 

Anti-Israel activist allegedly destroyed $60 million US military aircraft at Irish airport: feds

Ella Morrison, NY Post 11-17-26

An Irish anti-Israel activist allegedly destroyed a $60 million US warplane parked at an airport on the west coast of Ireland earlier this year in a meticulously planned attack, federal prosecutors announced Tuesday.

Irish national Daithi O’Corrain, 48, allegedly slipped past security and stormed onto the tarmac at Ireland’s Shannon Airport — a major transatlantic hub for the US military — on April 11, where he unleashed a wrath of carnage inside an empty US National Guard C-130 Hercules aircraft, according to the US Attorney’s Office, Southern District of New York.

A U.S. military C-130H aircraft parked on the tarmac at Shannon Airport.

Daithi O’Corrain, 48, allegedly destroyed a $60 million US National Guard C-130 Hercules aircraft in April. USDOJ

The instrument panel of a U.S. military C-130H aircraft with multiple smashed and shattered screens and gauges.

O’Corrain allegedly smashed every gauge in the cockpit. USDOJ

O’Corrain, who also goes by the name David Curran, breached the airport’s security perimeter, made his way to the American warplane, broke its locking mechanisms and then barricaded himself inside with a bunch of his own supplies, including ratchet straps and door hinges, court docs said.

The Irishman then proceeded to utterly destroy the warplane’s interior by cutting wire bundles and hydraulic lines, crimping a liquid oxygen line, smashing every gauge in the cockpit and puncturing air ducts, prosecutors alleged.

The deranged lunatic also brought multiple gallium capsules — a highly corrosive metal chemical that quickly eats through aluminum in minutes — onboard the primarily aluminum aircraft.

When the plane’s crew returned to the aircraft hours later to prepare for departure, they spotted O’Corrain through a window in the cockpit and quickly alerted security. 

Four orange ratchet straps with metal hooks, along with metal brackets, screws, and a bag of hardware.

O’Corrain allegedly barricaded himself inside the aircraft with a bunch of his own supplies, including ratchet straps and door hinges. USDOJ

Collage of two images showing a person standing on the tail of a C-130H aircraft at Shannon Airport.

He was spotted by the plane’s crew as they returned to the aircraft to prepare for departure. USDOJ

O’Corrain tried to escape out of a hatch on the plane’s roof and caused additional destruction by striking the exterior of the aircraft with an ax and pouring unknown substances and objects, including ball bearings, into the fuel tanks, according to court docs.

The wacko was nabbed by Irish authorities shortly after.

Damage to the body of a C-130H aircraft.

O’Corrain caused additional carnage to the exterior of the aircraft with an ax as he was trying to escape. USDOJ

Following the attack, the multi-million-dollar aircraft was deemed to be a total loss and will not return to active flight status.  

O’Corrain is accused of meticulously planning the costly vandalism and preparing for months — including researching the plane’s construction, purchasing gallium and searching for coordinates for where to breach the airport’s security perimeter.

Interior of a U.S. military C-130H aircraft.

The Irish national barricaded himself inside the aircraft. USDOJ

He also subscribed to a mobile app that tracks aircraft movement, including military planes, and researched previous attacks on US military aircraft.

O’Corrain was charged with destruction of government property, which carries a maximum sentence of 10 years in prison, according to the US Attorney’s Office.

Close-up view of severed wires and damaged electrical harnesses inside the C-130H aircraft.

O’Corrain allegedly cut wire bundles and hydraulic lines inside the military plane. USDOJ

“This was not an act of spontaneous vandalism. The defendant allegedly spent months researching the aircraft, acquiring tools and materials, and preparing to maximize the destruction he could inflict,” FBI Assistant Director in Charge James C. Barnacle, Jr. said.

Barnacle also noted O’Corrain caused “tens of millions of dollars in damage and jeopardiz[ed] critical military operations.”

“These charges send a clear and powerful message that attacks on U.S. military assets—and thus our national security—will not be tolerated,” US Attorney Jamie McDonald warned.

O’Corrain, who is being held at an Irish prison, is described as an “independent peace activist,” according to an online fundraiser raising money for his legal defense. 

“On April 11th 2026 an inspiring act of direct action was carried out at Shannon Airport to resist the unwanted presence of the US Military in Ireland in the face of their illegal war & support of Israel’s genocide,” the fundraiser said.

Your Local Epidemiologist, 11-18-26

It continues to make me angry that because of conspiracy theories and sheer ignorance,  people still prefer to let their kids suffer from measles rather than get them vaccinated. The same goes for COVID vaccinations and wearing masks. I just don't get it.

Here's Your Local Epidemiologist Katelyn Jetelina on the preventable loss of U.S. measles elimination status.

-------------------------------------

The U.S. lost measles elimination after 26 years. Now what?

Why it happened, who’s at risk, and what it’ll take to get it back

Katelyn Jetelina, 11-18-26

Welp, it’s official. The U.S. has lost its measles elimination status, setting the country back roughly 26 years. While losing this status is largely symbolic (it doesn’t trigger penalties, sanctions, or lost funding), it boils down to one simple, incredibly depressing thing: more preventable suffering.

Depending on where you live on the internet, you’re likely seeing messages that teeter between “no one can have a baby right now” and “measles isn’t a big deal.” As always, both miss the nuance about what it actually means.

So here’s what this means for you (and the country), what it doesn’t, and what it’ll take to crawl out of this hot mess.

What it means (for the country)

  • Measles is spreading here on its own again. Think of it like a forest fire. For nearly 26 years, the U.S. was mostly green and damp because vaccination rates were high. Sparks occasionally flew when someone traveled abroad and brought measles back (not from illegal immigration), but those sparks landed on wet ground so they fizzled. Now the forest has dried out in patches, communities where vaccination has decreased dramatically. When a spark lands there, it spreads like wildfire because this is the most contagious virus on earth. The embers are thrown into the next dry patch, and the next. Losing elimination status means fire has been burning somewhere in the country for over a year.

  • This happened for one simple reason: vaccination rates have fallen in too many communities. We can see this from two main angles:

    • Vaccines and prior immunity continue to work. Outbreak data from local health departments show 90-95% of cases are among unvaccinated or under-vaccinated.

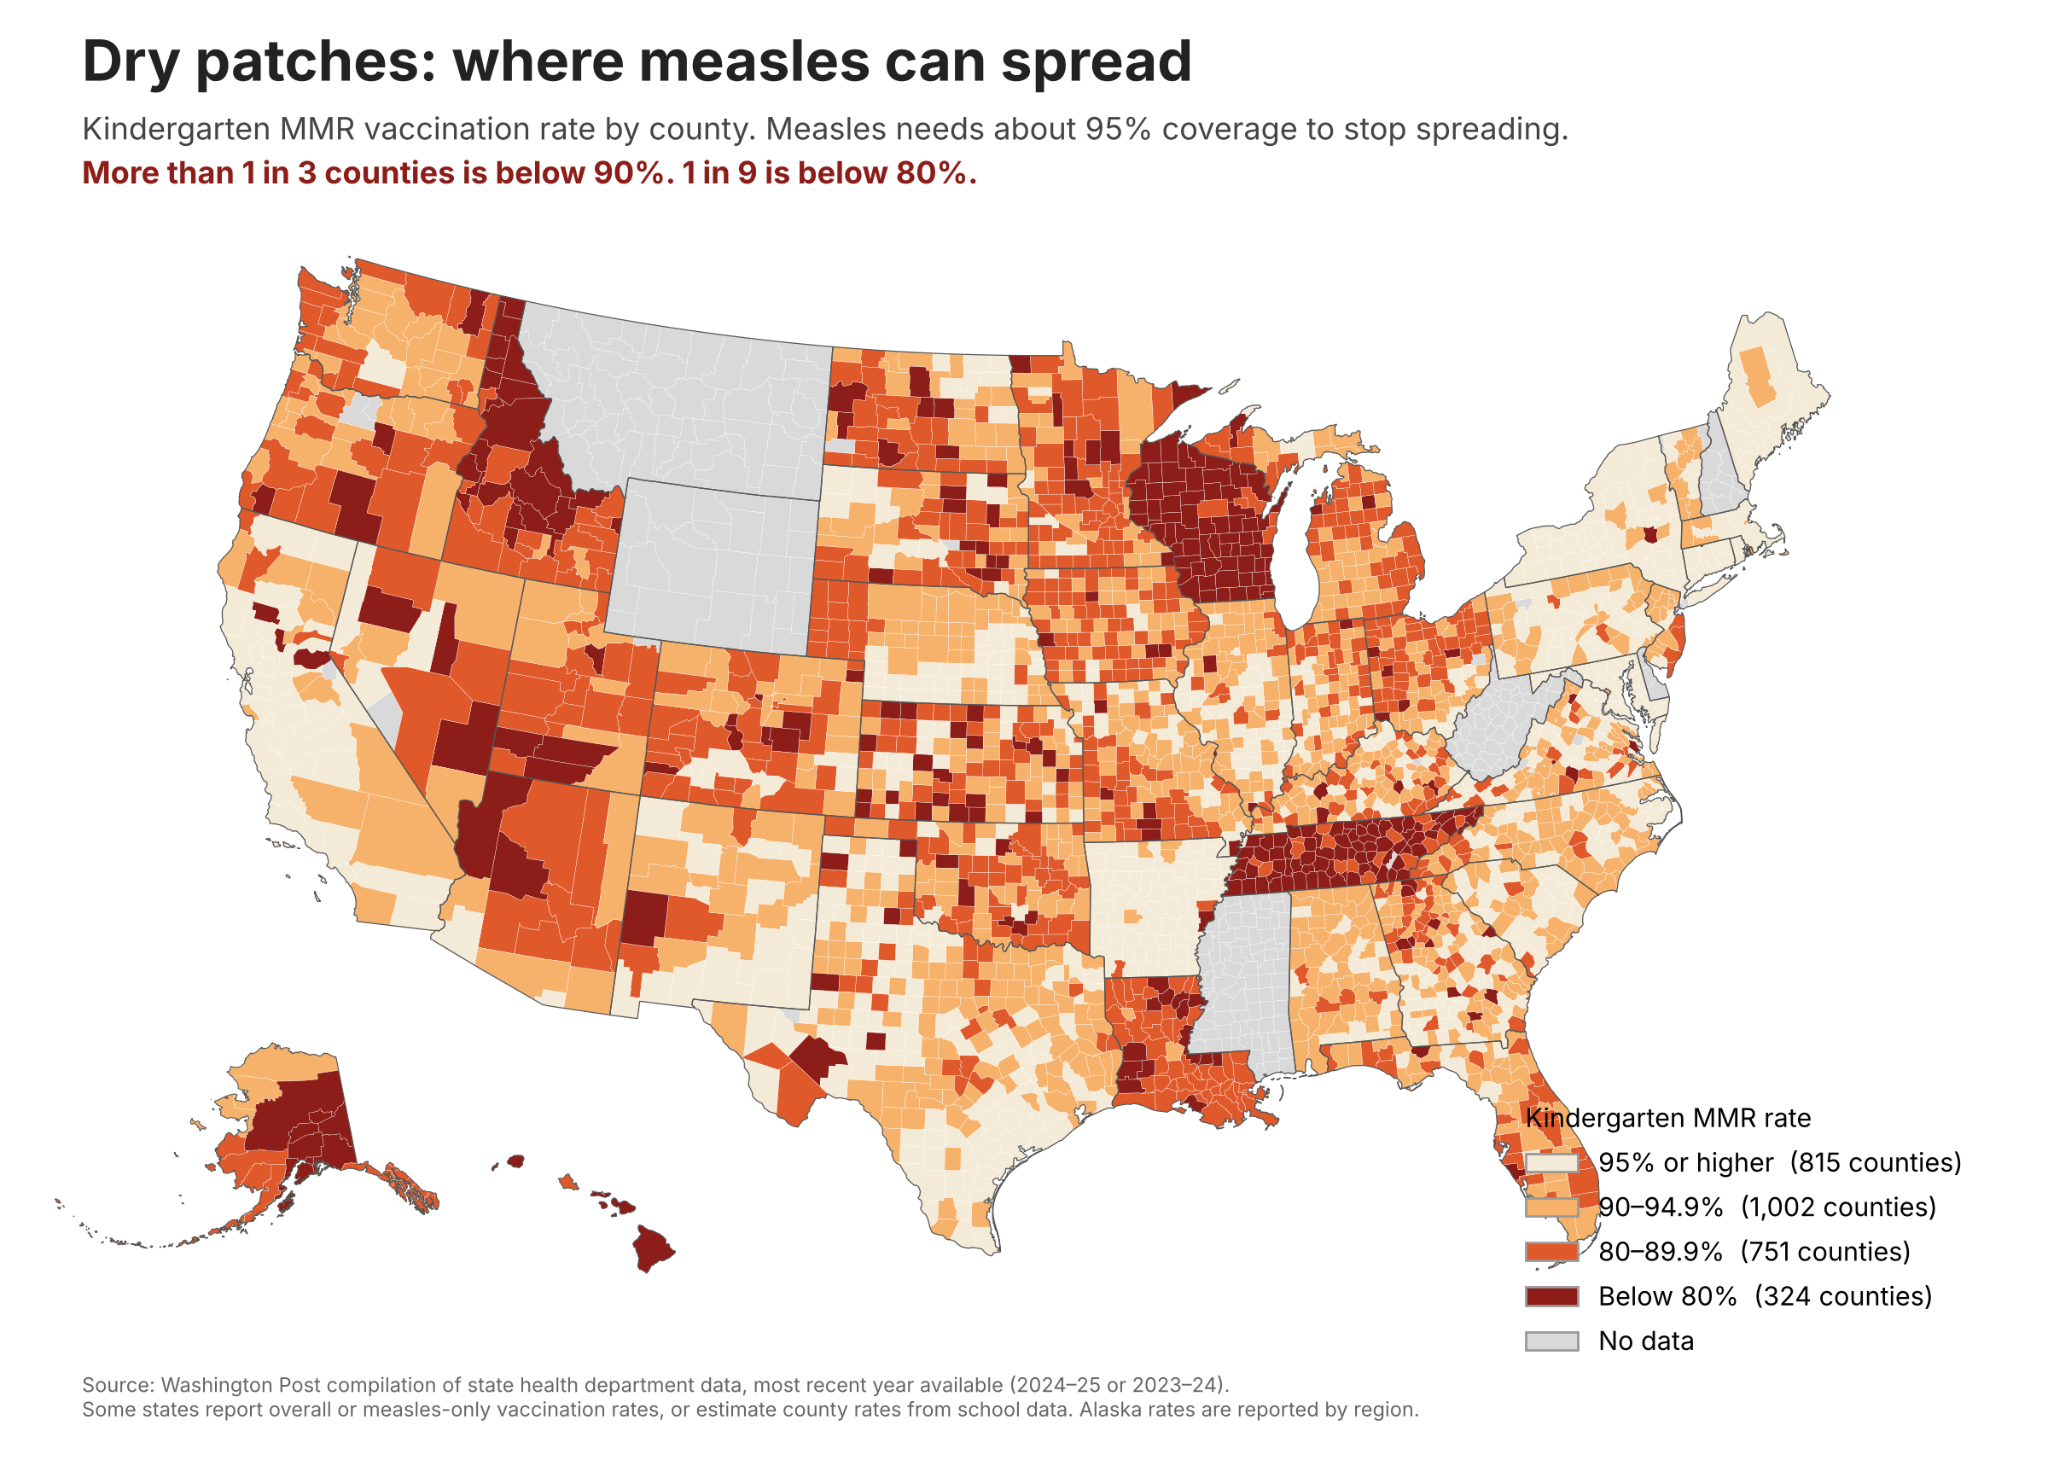
    • Vaccination rates are slipping. Fewer kindergarteners are getting vaccinated, and more people are opting for school vaccine exemptions. According to a database The Washington Post compiled, more than 28% of counties are below a 90% MMR vaccination rate. (We need 95% for herd immunity).

Figure created by Your Local Epidemiologist using The Washington Post's GitHub and Claude.
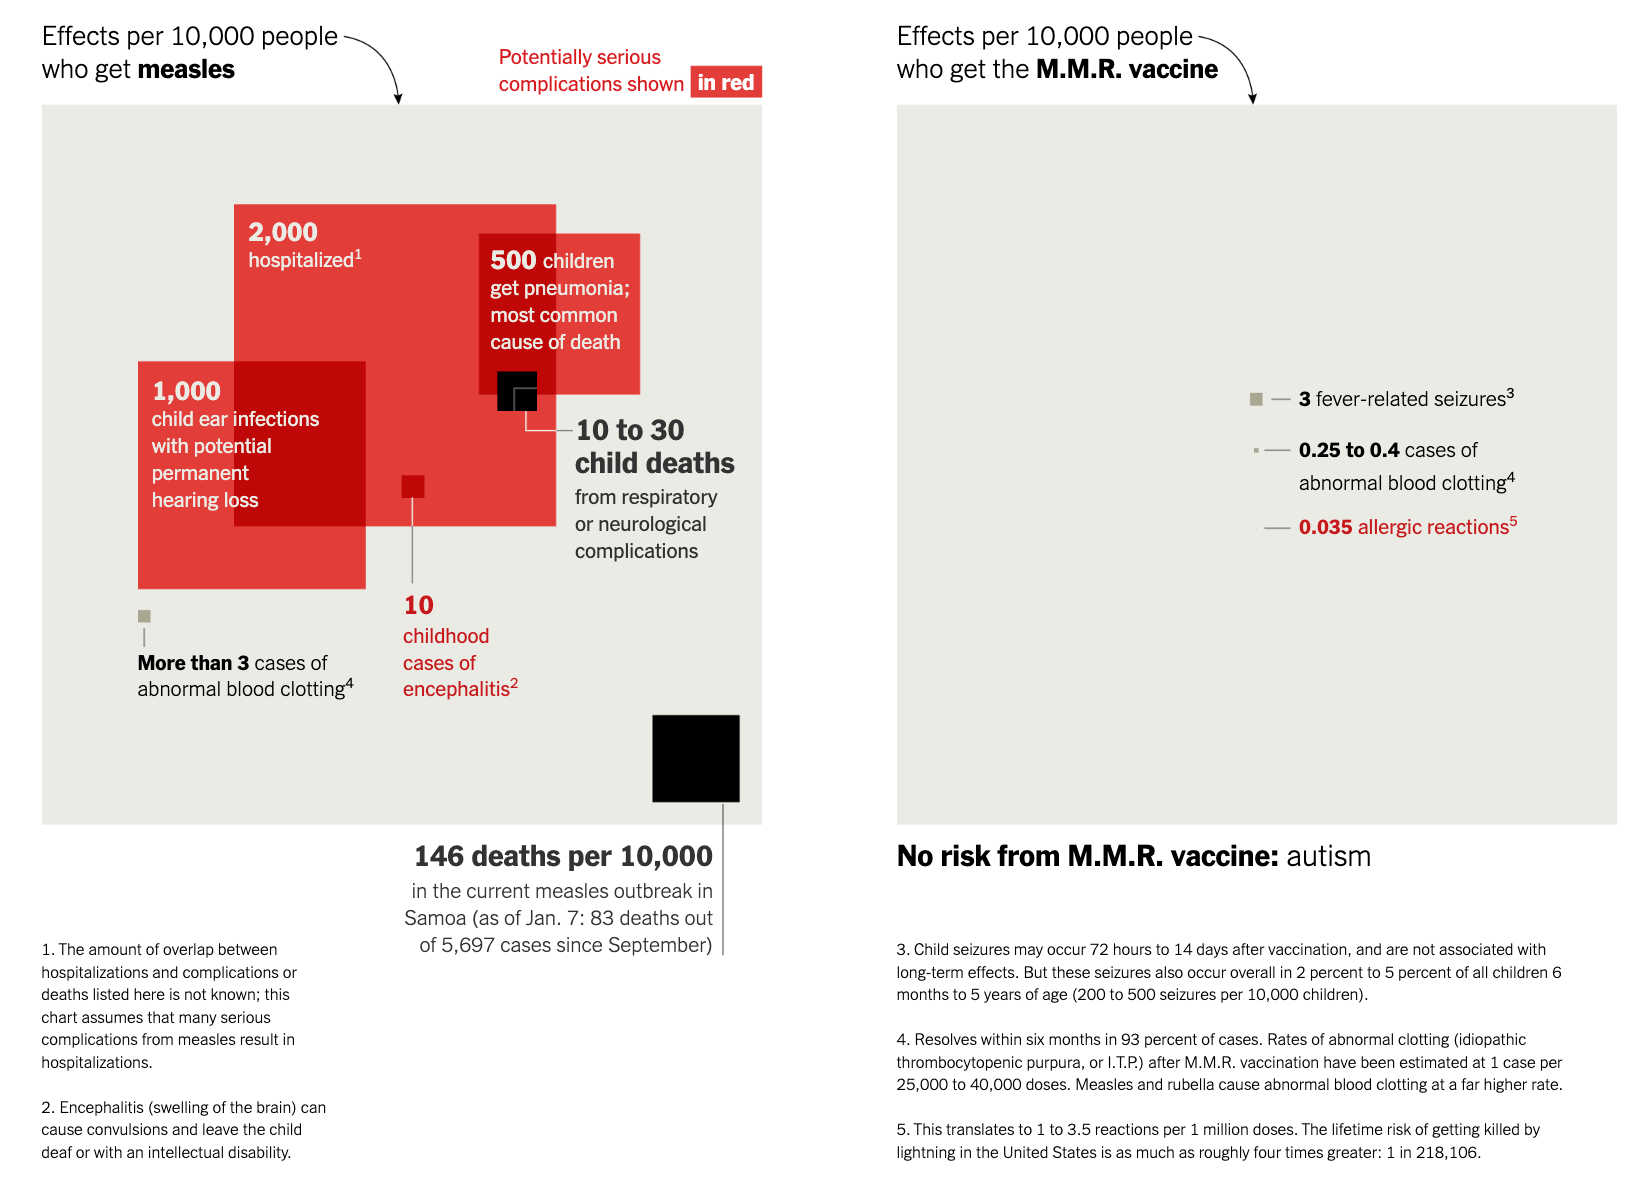
  • More people will suffer, especially kids. Those dry patches of forest will lead to more frequent, longer outbreaks. This means more rashes, yes, but also more preventable illness, hospitalizations, health care costs, and school absences among the unvaccinated. And this typically affects the most vulnerable: children. Just this year, we have had 5,412 cases and 10 deaths, which translates to:

    • ~271 cases of pneumonia

    • ~103,000 school days missed

    • ~5 kids with permanent hearing loss or brain damage from encephalitis

    • Many losing immunity to other viruses for 2–3 years (immune amnesia)

    • ~2 kids who will die years from now of SSPE, a fatal brain disease

    • ~$477 million in costs, including $13 million in direct medicare care, $301m in public health response, and $162m in lost productivity

This pales in comparison to the vaccine’s risks.

  • This has happened because of a myriad of factors, some brewing for decades and some new:

    • General amnesia. Vaccines are victims of their own success. Most people have never seen measles, or have forgotten what it looks and feels like.

    • Institutional mistrust. Faith in public institutions has eroded.

    • Information ecosystem changing. Influence has shifted away from physicians and evidence toward whoever is loudest online. Networks are also making a lot of money by spreading fear or doubt.

    • Measles recurrence. The disease flares up every 5-ish years, for reasons epidemiologists don’t really know.

    • NEW: A federal government that isn’t taking this seriously and, in some cases, is actively working against public health. (More below).

What it means (for you)

  • Measles is not everywhere, but stay informed. It’s not like the flu, which you can get at any grocery store. It is still concentrated in these pockets of the “forest.” But depending on where you live (and the hyperlocal vaccination rates of your county or school), an outbreak may be coming soon. Sign up for notifications from your local health department. Your school may send notifications, too. Also ask about your local vaccination rate.

  • If you’re up to date on your vaccines, you are very well protected. Really, truly. This doesn’t have to be one of the top 10 things you worry about. A breakthrough case is rare (3 in 100) and much milder. The vaccine stops transmission well, too.

  • Know if you might need another dose. Adults born before 1957 are generally considered immune. (They were exposed to “natural” infection.) People vaccinated between 1963 and 1967 may have received a less effective vaccine and should ask their doctor about another dose. If you don’t have records, it may make sense to just get another vaccine. See more information in these FAQs I answered last year:

10 FAQs on MMR and Measles Protection

·
March 14, 2025
10 FAQs on MMR and Measles Protection

With measles cases rising across the country, I’ve been getting a lot of questions (especially after that Hannity interview yesterday)! Here are your top 10 answered.

  • If an outbreak is near you:

    • Call your doctor if your family may have been exposed to measles. Call before visiting to avoid exposing others.

    • Know the signs of measles. Measles often starts with a high fever, cough, runny nose, and red, watery eyes, and then a rash that spreads down the body.

    • If you have symptoms (i.e., a rare breakthrough case), a public health department may call you to conduct an interview, and this data is critical to stopping the spread. Please be kind and work with them. They are on your side.

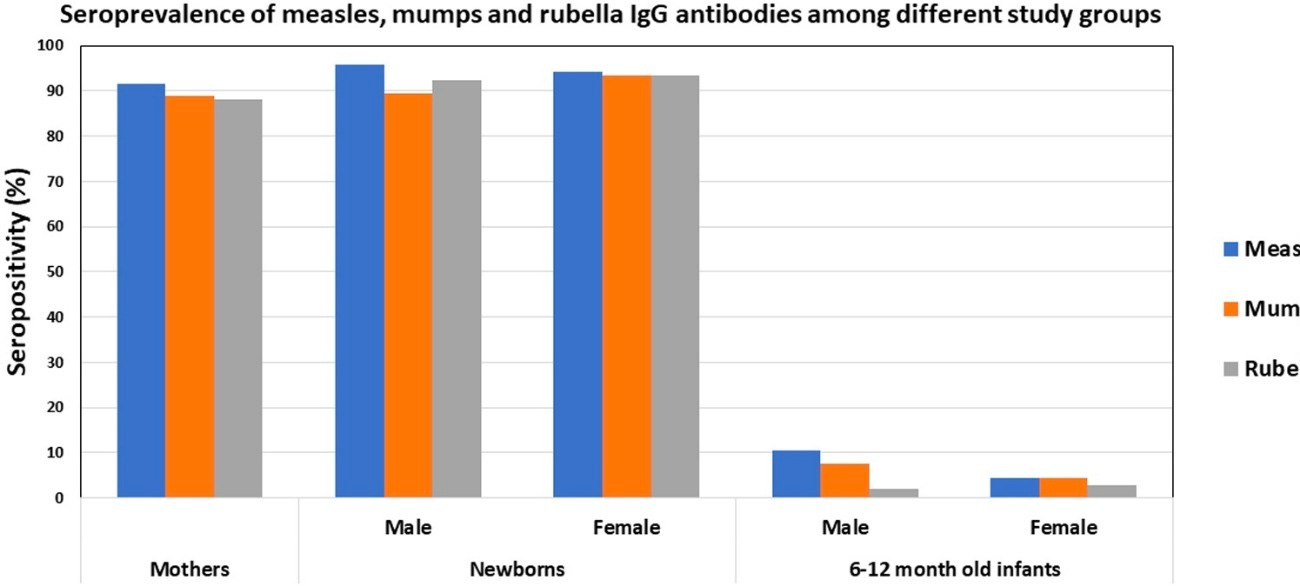
    • If you have an infant, ask your pediatrician for an early dose. Infants six to 11 months are eligible. This is considered a “Dose Zero.” They will still need another dose at 12 months and again at 4-5 years.

    • If you’re not vaccinated, act fast after exposure. Getting the MMR vaccine within 72 hours (or immune globulin within 6 days for some people) can prevent or lessen illness.

What it’ll take to crawl out: A plan and team effort

We can get this status back. Many other countries have fallen and then regained status. (Venezuela and Brazil each took about five years to regain their status.) To do this, the U.S. would need at least 12 straight months without continuous spread.

This will require a few things from multiple angles:

Strong federal leadership

This country needs a plan to fix what went wrong, and fund stronger vaccination, surveillance, and outbreak response. That means the federal leadership must take this signal seriously (which they haven’t for the past two years), through actions like:

  1. Sharing information openly, rather than suppressing it (as has happened with measles deaths and the risks of measles during pregnancy).

  2. Ongoing, clear public communication, instead of sowing doubt, providing alternative treatments like Vitamin A, or spreading fear, like claims that kids are “pumped full of vaccines.” Keeping false information off the CDC website, instead of posting things like the MMR vaccine causes autism (it doesn’t), would be a great start.

  3. Funding local and state public health departments, rather than demolishing the systems.

The CDC Director has already said losing the status won’t change how the administration handles measles. RFK Jr. says his plan is to double down on treatment (for which physicians have very few options).

That tells me we will be here for a while.

Support our public health “firefighters”

Public health workers in local and state jurisdictions will continue to spend enormous time stopping these outbreaks. They are the firefighters in this forest. Every second they spend doing that means fewer resources and less capacity to focus elsewhere on keeping communities healthy, like clean air, clean water, or opioids.

Advocate for stronger local, state, and federal public health infrastructure and leadership. Also, send them a note of appreciation.

A society-wide team effort

You have more influence on your community and family than you may realize. During the pandemic, 30% of unvaccinated people got vaccinated because of conversations they had with family and friends. That’s not nothing!

Try to be patient when having tough conversations with family and loved ones who may be hesitant about vaccines. You won’t change someone’s mind on the first try; the goal is for them to keep coming back to you with questions. Approach the conversation with deep curiosity and empathy (and try to align with their values). Shame-based messaging comes from genuine, valid frustration, but it doesn’t build a new foundation of trust.

For those on the front lines, a lot of people have a lot of questions, concerns and confusion. Below are a few resources the YLE team put together for paid subscribers that may help support your community, including a one-pager for clinicians to hand out to patients, talking points for Christian communities of faith, and top MMR protection questions.

Feel free to print out, share, and distribute.

Bottom line

The U.S. reached a heartbreaking milestone: we're back to a fire we put out more than 26 years ago. This means measles is spreading in communities where vaccination has slipped, and will cause harm. Getting back to elimination will take years and leadership we don’t have right now, but we’ve done it before, and we can do it again.

It will take all of us.

Love, YLE

-----------

Your Local Epidemiologist (YLE) comprises a team of experts, ranging from physicians to immunologists to epidemiologists to nutritionists, working together with one goal: to “translate” ever-evolving public health science so that people are well-equipped to make evidence-based decisions. The YLE suite of newsletters reaches over 475,000 people across more than 132 countries. This newsletter is free to everyone, thanks to the generous support of fellow YLE community members.